

Don’t it always seem to go that you don’t know what you’ve got till it’s gone…
Joni Mitchell, Big Yellow Taxi
Before we get to Joni Mitchell, food noise and GLP-1 drugs, let’s talk about Karl-Anthony Towns, aka KAT. I’m a sucker for a sports redemption story, and Towns and the newly-minted NBA-champion Knicks, the franchise winning its first title since 1973, were as good as those stories get.
But now I want to talk about KAT’s eating behavior in his teenage years, which is more the fodder of this Substack. KAT was already 6’ 3” by the time he was in fifth grade; he grew to 7’ and 250 pounds by his one-and-done college season at Kentucky. As a consequence, he exhibited the kind of voracious appetite that, absent context, would be called hyperphagia in the obesity science world.
Here’s how it was described in 2015 in The New York Times:
There just never seemed to be enough food to satiate Towns’s growing body. After school, he would eat a footlong sub before his mother’s home-cooked dinners, even after having a hefty lunch of homemade chicken, rice and vegetables and his favorite snacks, granola bars and Buncha Crunch.
So why did I say (and italicize) absent context above, about whether this constituted hyperphagia? Because this voracity is expected for a growing child, particularly one on a 7’ tall, 250 pound trajectory. In that context, it’s normophagia. We’d all agree that a voracious appetite is a healthy response to the demands of the growing body. Never enough food to satiate it.
But here’s where it waxes paradoxical. If Towns had maxed out at 6’0, 250, that identical appetite becomes hyperphagia—excessive—even though body weight is also identical. Now the voracious appetite is assumed to cause the excessive “growth,” albeit mostly fat, horizontal rather than vertical. We’ve flipped the causality.
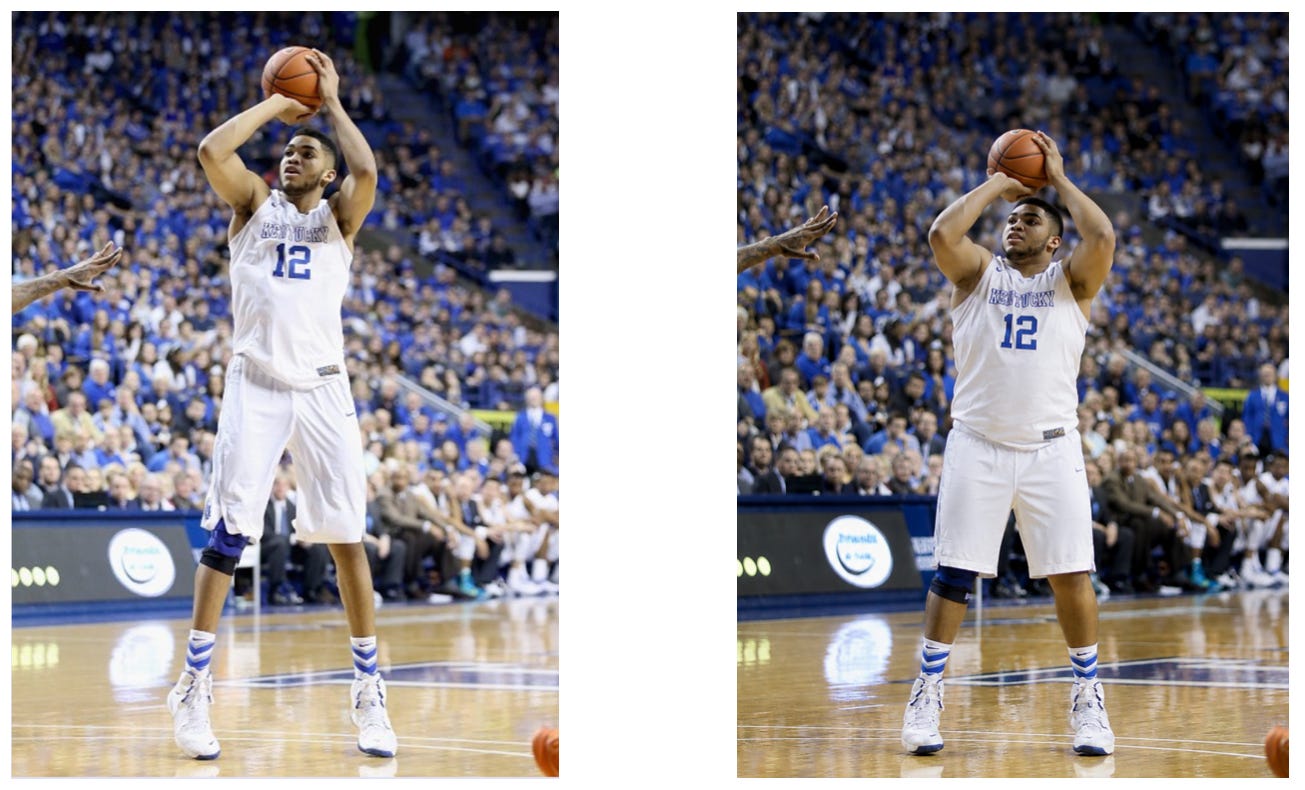
That context-dependent causality flip is one of the more (throat-clearing) peculiar implications of how we think about obesity. Growing children: growth drives appetite. Fattening children: appetite drives growth.
Ok, paradoxical, you’re thinking, but what’s the connection to food noise?
I’m going to assume that Towns thought about food and his next meal a lot in those years, certainly far more than his far shorter peers.1 He might have even thought about his next meal while he was eating his current one, his mother’s home-cooked dinners after his foot-long sub. He would almost always have been hungry, and so almost always thinking about how to satisfy that hunger. What could be more natural?
If so, Towns was experiencing what is currently known as food noise—defined simply as intrusive thoughts about food. But this wouldn’t have been a subject for scientific study because 1) Towns was a very growing child, so we expect him to be eating-obsessed; 2) Towns (the real one) was not obese, and so we can’t blame his obesity on the food noise; and 3) he wasn’t taking GLP-1 drugs that make the food noise go away.
So who cares if KAT thought about food all the time, even while he was eating?
Short answer: I do, because I think it tells us something meaningful, weirdly, about how GLP-1 weight loss drugs might work, or at least why they might inhibit food noise and quiet cravings. KAT would have thought about food all the time, because he was hungry all the time, and he was hungry because he was growing so large.
The obvious question is whether the same might be true of the food noise experienced by people with obesity. What if they’re always at least a little bit hungry, even if they don’t think of it that way? Hunger, after all, is not necessarily a conscious experience so much as a physiological state. And what if the drugs get rid of the food noise because they inhibit that hunger, as they surely seem to do?
One way to think about it is that people who take these drugs behave as though they’re satiated. Rather than acting as if they’re always at least a little bit hungry, they act as though they’ve just had a big meal and are uninterested in another bite. So the question becomes: do the drugs fool their brains into thinking they’re satiated, which is the conventional wisdom (more or less), or do the drugs actually satiate them?
The latter would be the simpler hypothesis: they act like they’re satiated because, well, they are. They stop thinking about eating all the time because their bodies are satisfied with the fuel they have. But how could that be true, when we also know they’re eating less than ever, perhaps even semi-starving themselves?
There is at least one way, but it requires buying into a conception of hunger that was beginning to be embraced in the 1980s and early 1990s, before leptin was discovered and obesity research became a subdiscipline of molecular biology and genetics. It emerged from the animal experiments that researchers in the discipline of physiological psychology had to conduct to understand the physiological basis of fundamental behaviors, most obviously eating and drinking. The leptin-focused obesity researchers who came after 1994 not only didn’t do these kinds of experiments, they didn’t read the literature of the physiological psychologists who did. They were simply unaware of that work, unaware of its relevance to their interests (which, regrettably, happen to be our interests), as they still are.
A brief note on paradigm bubbles
One characteristic of the scientific enterprise is that it has always had schools of thought competing with one another. Each school emerges from a particular way of thinking about a problem and is led by researchers who develop those ideas and do the experiments to test them. These thought schools can win out because they’re right, which is the ideal. But they can also win because they’re the most popular, generate the most funding, or because the researchers leading them are at more prestigious institutions and have better connections with the media. They have the better PR.
If science journalists like myself come along and interview enough researchers on a single story, we might stumble upon a school of thought that never won a majority—a kind of paradigm bubble. Within it, researchers will have developed a theory at odds with the reigning narrative and, so they think, done the experiments to test it. But they never make progress in getting their ideas embraced, for the kinds of reasons I discussed in my “One of Us Stinks” post back in April. Most obviously: if they’re right, the influential and respected leaders of the other schools of thought, and their students, are not.
The journalist’s job is to assess the validity of the ideas inside the bubble, but it’s difficult to get anyone outside to say anything more generous than “they could be right, but I doubt it.” Hence these bubbles, with precious few exceptions, tend to remain bubbles, and eventually to evaporate as the founders of the school retire and pass away—science progressing (or maybe retrogressing) funeral by funeral, as the saying goes—and the students shift their focus to survive, because there’s no demand outside the bubble for the work they did inside it.
The concept I’m going to discuss now, about the connection between hunger, food noise and GLP-1s, exists in one of these paradigm bubbles. If it’s right, then these drugs very likely inhibit food noise and abolish cravings not because they quiet them in the brain, but because they almost literally feed the liver.
